What are gallbladder stones?
The gallbladder is a small pouch under the liver that stores bile, a digestive juice that helps break down fat. Gallstones form when substances in bile, mainly cholesterol or bile pigment, harden into stones. They range from grains of sand to stones a few centimetres across, single or many.
Gallstones are common, and many people find out about them by chance on an ultrasound done for something else. Risk is higher in women, after pregnancy, with age, with obesity or diabetes, after rapid weight loss, and when others in the family have had stones.
When a stone blocks the outlet of the gallbladder, it causes biliary colic:
- Pain in the upper right or upper middle abdomen, often spreading to the back or the right shoulder blade
- Pain that builds up, lasts from about 30 minutes to a few hours, then eases
- Attacks that often come in the evening or at night, sometimes after a heavy or oily meal
- Nausea or vomiting with the pain
Bloating, burping and acidity are often blamed on gallstones, but these vague symptoms are just as common in people without stones. Part of the consultation is working out whether your symptoms really come from the gallbladder.
When do you need surgery?
Stones that have never caused symptoms usually do not need an operation, and most people with silent stones never develop problems. Surgery may still be advised in a few situations, such as a very large stone, a thickened or calcified gallbladder wall, or a sizeable gallbladder polyp. Dr. Sanjit Gogoi will tell you if any of these apply to you.
Once gallstones cause symptoms, guidelines such as those from NICE recommend laparoscopic removal of the gallbladder, because attacks tend to return and complications become more likely:
- Acute cholecystitis: an inflamed, often infected gallbladder, with constant pain, tenderness and fever
- Common bile duct (CBD) stones: a stone slips into the main bile duct, causing jaundice, dark urine and pale stools
- Cholangitis: infection of a blocked bile duct, a serious condition
- Gallstone pancreatitis: inflammation of the pancreas triggered by a passing stone, which can be severe
Diagnosis: what happens at the consultation
Dr. Sanjit asks about the pattern of your pain, examines your abdomen and goes through your reports with you in plain words. The usual tests are:
- Ultrasound abdomen: the main test for gallstones. It shows the stones, the gallbladder wall and the width of the bile duct.
- Liver function tests (LFT) and blood tests: raised bilirubin or liver enzymes suggest a stone in the bile duct. Blood count and amylase or lipase help when infection or pancreatitis is suspected.
- MRCP: a special MRI of the bile ducts, done when a duct stone is suspected.
- Fitness tests: routine blood tests, ECG and, where needed, a chest X-ray or physician review before anaesthesia.
Endoscopic ultrasound or a CT scan is used in selected cases. You leave knowing what the stones are doing, whether surgery is advised, and when.
Treatment options
Laparoscopic cholecystectomy
Removing the whole gallbladder with its stones is the standard treatment for symptomatic gallstones, and it is done by laparoscopic (keyhole) surgery in most patients. You can live normally without a gallbladder: bile simply flows from the liver straight into the intestine.
Why not remove only the stones?
Taking out the stones and leaving the gallbladder is not done, because a gallbladder that formed stones tends to form them again. Tablets that dissolve stones (ursodeoxycholic acid) work only for small cholesterol stones, take months, and stones often return when the tablets stop. Read more in can gallbladder stones go away on their own?
Watchful waiting
For silent stones, or for some patients whose health makes surgery risky, waiting with clear warning signs is a valid choice. A low-fat diet may reduce attacks, but it does not remove the stones.
Stones in the bile duct
A stone in the common bile duct is usually cleared by ERCP, an endoscopic procedure done through the mouth by a gastroenterologist, without cuts. The gallbladder is then removed laparoscopically, often in the same admission or soon after.
Complicated and inflamed gallbladders
With acute cholecystitis, early laparoscopic surgery, ideally within about a week of the attack, is recommended for suitable patients. If the attack is older, some patients settle on antibiotics first and are operated on a few weeks later. A gallbladder inflamed many times can be scarred and stuck, which makes surgery harder. Complicated gallbladder surgery is a regular part of Dr. Sanjit's work. In very inflamed cases, removing most of the gallbladder (subtotal cholecystectomy) can be the safer choice, to protect the bile duct.
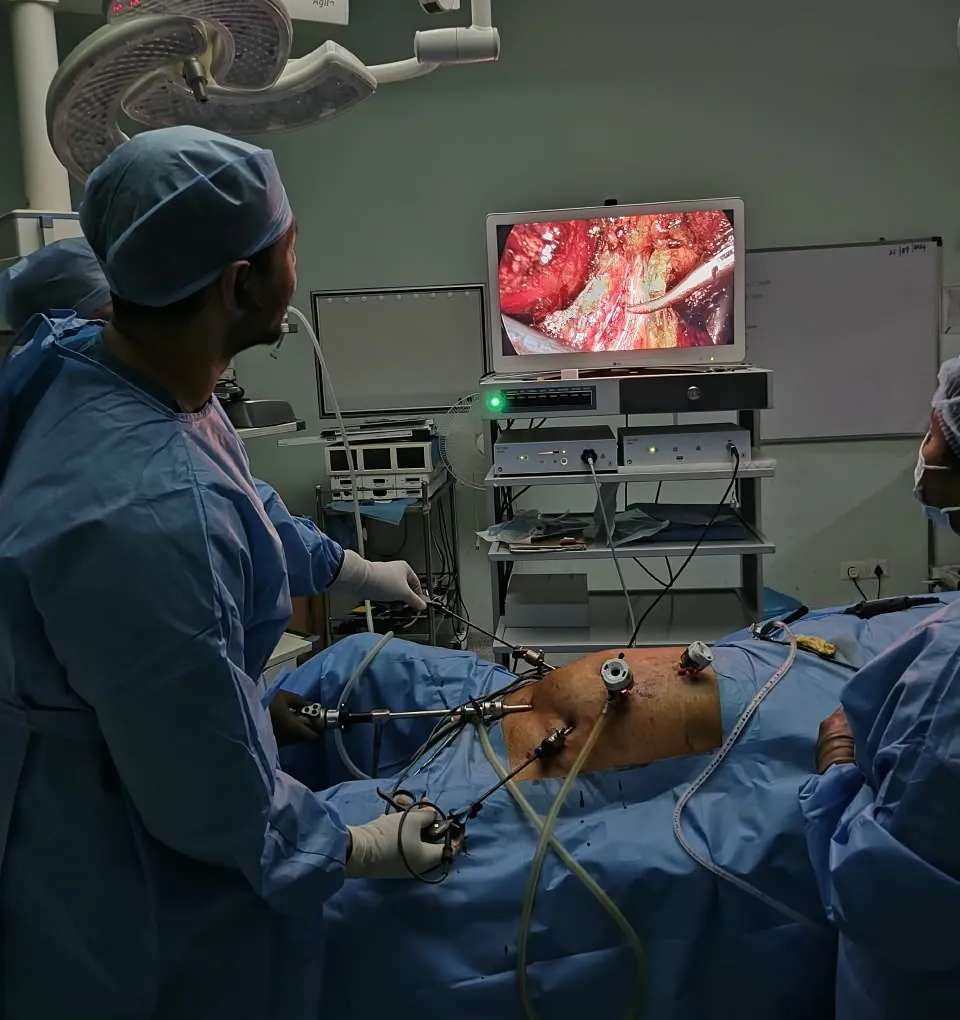
How laparoscopic cholecystectomy is done
- Anaesthesia: general anaesthesia, so you are asleep throughout.
- Ports: three or four small cuts, usually one at the belly button (about 10 mm) and the others 5 to 10 mm in the upper abdomen.
- Gas and camera: the abdomen is gently filled with carbon dioxide to create space, and a camera gives a magnified view on a screen.
- Safe identification: the tissues are carefully separated to identify the cystic duct and artery before anything is divided. This step, the "critical view of safety", is the main protection for the bile duct.
- Removal: the duct and artery are clipped and divided, the gallbladder is freed from the liver and taken out in a bag through the belly button port.
- Closure: the gas is released and the cuts are closed with dissolving stitches or skin glue.
A routine operation usually takes about 45 to 90 minutes. Inflamed or scarred gallbladders take longer.
Conversion to open surgery means switching to a larger cut during the operation. It happens in a small proportion of planned operations and more often with acute inflammation. It is a safety decision, made when the anatomy cannot be seen clearly through the camera, not a failure. You are told about this possibility before you consent.
Recovery and diet after surgery
| When | What to expect |
|---|---|
| Day of surgery | Walking within a few hours; sips of water, then light food. |
| Same day or next | Most patients go home the same day or the next morning, on simple painkillers. |
| Days 2–7 | Port-site soreness and a shoulder-tip ache from the gas settle. Short walks every day. |
| Weeks 1–2 | Most people return to desk work and can drive or ride once they can brake comfortably. |
| About 4 weeks | Heavy lifting, gym work and lifting gas cylinders, as per your written plan. |
Diet after gallbladder removal
Most people return to a normal diet within a few weeks, and there is no lifelong special diet. In the first weeks:
- Start with light, home-cooked food such as idli, curd rice, khichdi, dal and soft vegetables
- Eat smaller meals more often instead of one large meal
- Go easy on fried and very oily food at first, then reintroduce it gradually
- Drink enough water and include fibre
Some people notice looser stools after fatty meals for a while. This usually settles; if it continues, tell Dr. Sanjit, as it can be treated.
Risks and how they are reduced
Laparoscopic cholecystectomy is one of the most commonly performed operations, and most patients recover without problems. Possible complications include:
- Port-site infection or bruising, usually minor
- Bleeding, rarely needing further treatment
- Bile leak from the liver bed or duct stump, uncommon, usually managed with a drain or ERCP
- Bile duct injury, rare (studies report a few cases per thousand operations) but serious, which is why careful identification of the anatomy matters
- A retained stone in the bile duct, which may need ERCP later
- Port-site hernia at the belly button, uncommon
- General risks of anaesthesia, chest infection and blood clots, reduced by early walking
Risks are reduced by careful assessment before surgery, the critical view of safety, a readiness to convert to open when needed, and clear advice on warning signs after you go home: fever, worsening pain, yellow eyes or a swollen abdomen.
Why patients from Sarjapur Road, HSR and Bellandur see Dr. Sanjit
Dr. Sanjit holds an MS in General Surgery and the MRCS from the Royal College of Surgeons of Edinburgh, with about 18 years in general, laparoscopic and laser surgery, including complicated and inflamed gallbladders. He has trained DNB surgical residents at Manipal Hospital and mentored more than 50 young surgeons in minimal access surgery.
He operates at SPARSH Hospital, Sarjapur Road, where he consults from 10 am to 5 pm, and sees patients from 5 pm to 8 pm at his evening clinic in Doddakannelli, Monday to Saturday. Both are on Sarjapur Main Road, about 20 to 30 minutes from HSR Layout, Bellandur and Koramangala. He explains your scan in simple terms and stays reachable by phone while you recover.
Cost of gallbladder surgery in Bangalore
The cost depends on whether the operation is planned or urgent, how inflamed the gallbladder is, whether ERCP is needed for duct stones, the hospital and your room category. See the gallbladder surgery cost page for indicative ranges, or send your ultrasound report for guidance.

MBBS, MS (General Surgery), MRCS (Edinburgh). General and Minimal Access Surgeon with about 18 years in general, laparoscopic and laser surgery. Consults at SPARSH Hospital, Sarjapur Road (10 am – 5 pm) and his evening clinic in Doddakannelli (5 – 8 pm). KMC Reg. No. 96096. More about Dr. Sanjit